












Iron infusions
Iron Deficiency Without Anaemia: Why New ASH Guidelines Reflect the Approach We Take at Effect Doctors
The American Society of Hematology has introduced new standards for diagnosing iron deficiency. At Effect Doctors, the underlying principle is one we have long applied in practice: iron deficiency should be investigated before waiting for anaemia to develop.
When someone presents with persistent fatigue, reduced exercise tolerance, headaches, dizziness or difficulty concentrating, one of the questions we often ask is whether iron deficiency could be contributing. The starting point is not simply: “Are you anaemic?” It is: “Do you have adequate iron stores?” That distinction matters.
The American Society of Hematology (ASH) has now published new clinical practice guidelines specifically addressing the diagnosis of iron deficiency, including in people who do not have anaemia. For adults, ASH recommends a ferritin threshold of 30 ng/mL or lower for diagnosing iron deficiency, with different thresholds in certain higher-risk and inflammatory settings.
For Effect Doctors, this is an important development because it reinforces an approach we believe is clinically useful: test for iron deficiency rather than simply waiting for iron-deficiency anaemia to appear.
Reviewed & Published by:
Dr William Turner
Dr William Turner

Dr William Turner
Dr Turner is a Consultant Anaesthetist and a fellow of the Royal College of Anaesthetists; he is a founding member of Effect Doctors.
Read BiographyAt Effect Doctors, we start with the question—not the treatment
Iron deficiency is common, but its presentation is not always straightforward.
Someone can have depleted iron stores while their haemoglobin remains within the normal laboratory range. A standard full blood count may therefore appear reassuring even though iron stores are low.
This is why our approach begins with assessment.
Where a patient’s symptoms and circumstances make iron deficiency a possibility, we can test ferritin rapidly and, where appropriate, undertake more comprehensive blood testing.
Our Rapid Ferritin Test uses a finger-prick sample and provides a result in approximately 15 minutes.
That gives us an immediate indication of whether depleted iron stores could be part of the clinical picture.
It also allows the next decision to be based on evidence rather than assumption.
Why we don’t simply wait for anaemia
Anaemia is not the definition of iron deficiency. Iron deficiency describes insufficient iron stores. Iron-deficiency anaemia occurs when iron availability has become sufficiently compromised to affect haemoglobin production.
There is therefore a stage at which iron stores may be depleted without established anaemia.
This distinction has been recognised clinically for some time. The British Society for Haematology has highlighted the complexity of diagnosing iron deficiency and the limitations of relying on any single laboratory measurement.
The significance of the new ASH guidance is that it provides clearer evidence-based clinical decision limits for diagnosing iron deficiency.
It therefore represents an important step towards standardising an approach that many clinicians have increasingly adopted: looking at iron status before a patient reaches the point of overt anaemia.
Ferritin is important—but it needs context
Ferritin is one of the most useful markers of the body’s stored iron.
Historically, however, there has been considerable variation in the thresholds used to define iron deficiency.
ASH now recommends a ferritin clinical decision limit of ≤30 ng/mL for adults. In some higher-risk groups, including menstruating and pregnant individuals with anaemia, a threshold of ≤50 ng/mL is recommended. Where inflammation is present, ferritin can be more difficult to interpret, and ASH recommends considering ferritin below 100 ng/mL or transferrin saturation below 20% in relevant circumstances.
This illustrates an important point about our approach at Effect Doctors: A ferritin result is not interpreted in isolation.
We consider it alongside symptoms, haemoglobin, other iron markers, medical history and the circumstances of the individual patient.
Finding iron deficiency is only the beginning
A low ferritin result raises another important question: Why is the patient iron deficient? There are many possible explanations.
These can include blood loss, menstrual losses, dietary factors, increased physiological requirements, gastrointestinal conditions and problems with absorption.
For some people, particularly where iron deficiency is recurrent or unexplained, identifying the underlying cause may be as important as replacing the iron itself.
This is why we do not approach iron deficiency simply as a problem of supplementation.
Our process is: Test → assess → understand the cause → treat appropriately → review.
That distinction is important.
When might intravenous iron be appropriate?
Finding a low ferritin does not automatically mean that intravenous iron is required.
For some patients, oral iron may be appropriate. For others, oral iron may not be tolerated, may not be absorbed effectively, may have failed to correct the deficiency, or iron replacement may need to be achieved more rapidly.
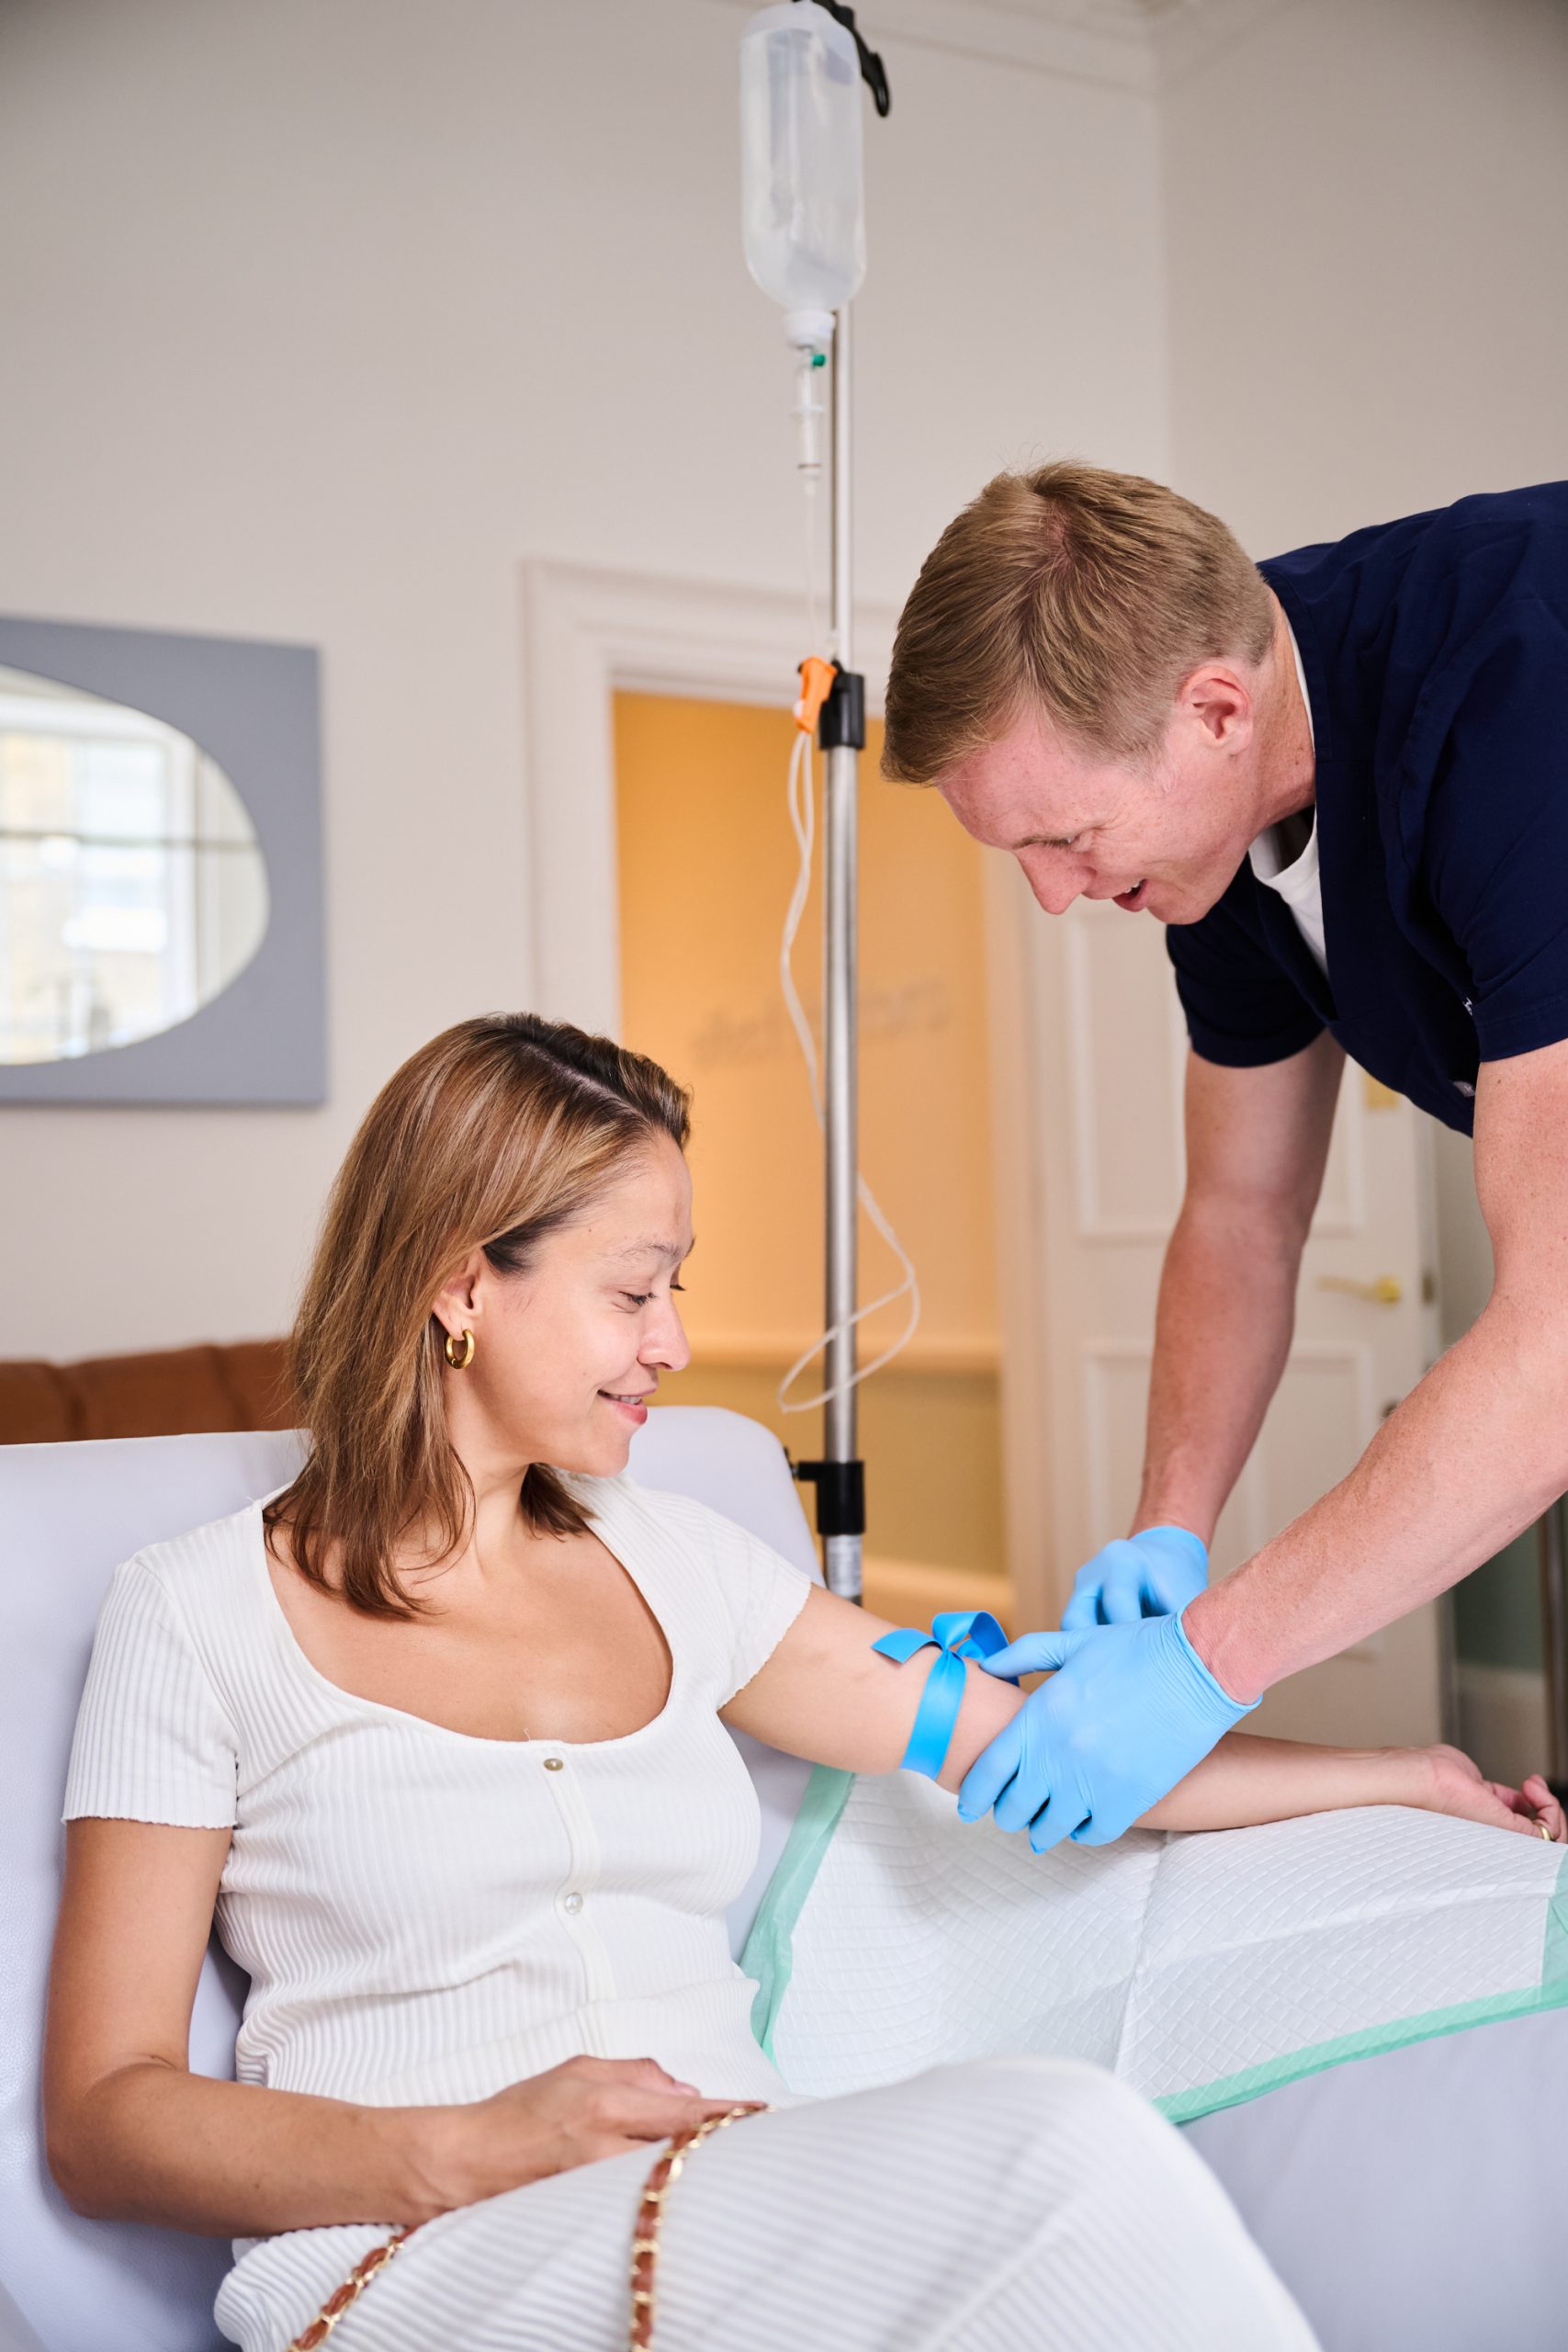
Where clinically appropriate, intravenous drips can provide an alternative route of iron replacement.
At Effect Doctors, intravenous iron is provided following medical assessment and appropriate blood testing. The treatment therefore follows the diagnosis—it does not replace it.
This is also why the new ASH announcement should not be interpreted as recommending iron infusions for everyone with a low ferritin. The new guidance concerns diagnosis; ASH has indicated that separate treatment guidance is expected in 2027.
Why the new ASH guidance matters
The importance of the announcement is therefore not simply that a new ferritin number has been published. It represents a broader recognition that iron deficiency and anaemia are not synonymous.
For patients, that distinction can be significant. Someone with persistent symptoms may have a normal haemoglobin result and still have depleted iron stores. Looking only for established anaemia can therefore miss an earlier stage of iron deficiency.
The new ASH guidance provides clearer clinical thresholds intended to reduce that problem. For clinicians already taking a more proactive approach to iron status, the announcement is less a completely new concept than a significant move towards greater consistency and standardisation.
Our approach at Effect Doctors
We believe healthcare should increasingly move towards identifying problems before they become more advanced, where appropriate testing can provide useful information and allow patients and doctors to make better-informed decisions.
Our approach to iron deficiency reflects that philosophy. Rather than asking only whether a patient is anaemic, we can investigate whether their iron stores are adequate.
Rather than assuming that fatigue has a single explanation, we can test for potential contributors.
And rather than moving directly from a blood result to treatment, we consider the wider clinical picture and, where appropriate, investigate why the deficiency has occurred.
For patients experiencing persistent or unexplained symptoms, a Rapid Ferritin Test can be a simple starting point.
Where the result indicates possible iron deficiency, this can be followed by more comprehensive testing and medical assessment.
The key message
You do not have to be anaemic to be iron deficient. The new ASH guidelines provide clearer standards for recognising this.
At Effect Doctors, our approach is to identify iron deficiency early, understand the clinical context and underlying cause, and then determine the most appropriate treatment for the individual patient.
That means looking beyond the question “Is my haemoglobin normal?” and asking the more useful question: “Are my iron stores adequate?”
Sources
American Society of Hematology, Clinical Practice Guidelines: Diagnosis of Iron Deficiency.
Recent effect insights

Iron infusions
IV drips
Choosing the right ingredient for your Iron Infusion
Why We Use Ferric Derisomaltose for All Our Iron Infusions
Iron deficiency is one of the most common nutritional deficiencies worl...
June 8, 2026

Iron infusions
Why “Optimum” Is Not the Same as “Normal” When Measuring Iron Levels in Women
Iron is a critical mineral for overall health, particularly for women who experience menstruation, pregnancy, or other factors that can d...
February 17, 2025

Iron infusions
Iron Deficiency and ADHD: What’s the Connection?
Emerging research suggests a link between iron deficiency and symptoms commonly associated with ADHD, such as brain fog, poor concentrati...
July 9, 2025